Cancer
Endoscopic Submucosal Dissection in Korea
Minimally invasive endoscopic removal of early GI tumors — Korea leads globally in ESD volume and expertise.
Quick Answer
- ESD removes early-stage tumors of the stomach, colon, or esophagus without open surgery, via a flexible endoscope.
- Korea performs ESD at exceptionally high national volume — roughly one-third of early gastric cancers in Korea are treated this way.
- Procedure takes 1–3 hours; most patients stay 1–3 nights and can return home within 1–2 weeks.
At a Glance
| Procedure time | 1–3 hours |
|---|---|
| Anesthesia | Propofol-based sedation (monitored) or general anesthesia |
| Hospital stay | 1–3 nights (gastric); may extend to 3–5 nights for complex colorectal cases |
| Recommended stay in Korea | 7–14 days for follow-up endoscopy and pathology review |
| Recovery | Soft diet 1–2 weeks; return to desk work ~5 days; strenuous activity at 2–4 weeks |
Overview
Endoscopic Submucosal Dissection (ESD) is a minimally invasive endoscopic technique for removing early-stage gastrointestinal (GI) tumors in one piece — a process called en bloc resection.
It targets lesions in the stomach, esophagus, colon, and rectum that have not yet penetrated deeply into the gut wall. Because the tumor is resected rather than destroyed, the removed specimen can be evaluated precisely under a microscope, helping doctors confirm complete removal.
ESD was pioneered in Japan and then refined heavily in South Korea, where Korea's very high rate of early gastric cancer detection — supported by the national screening program — created a large, sustained caseload that drove rapid technique improvement.
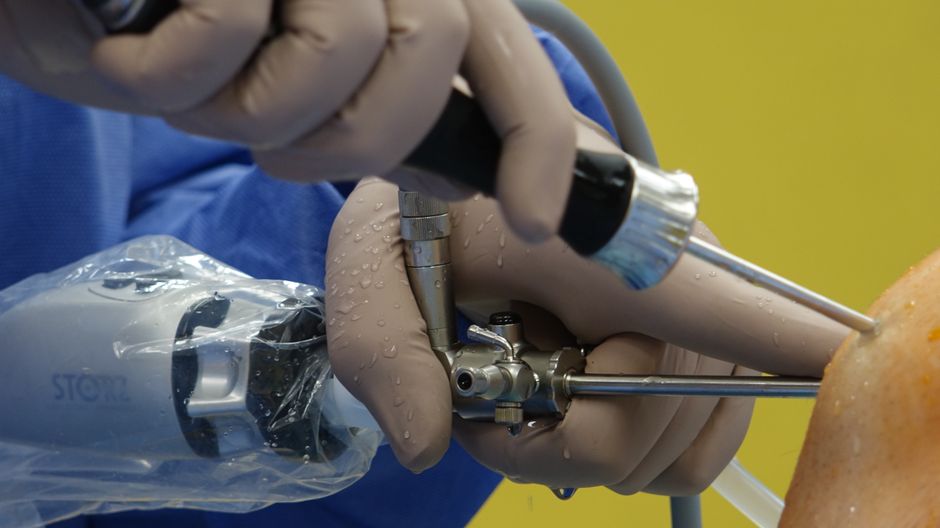
Unlike open surgery or laparoscopy, ESD leaves no abdominal incisions. The endoscope is inserted through the mouth (upper GI) or anus (lower GI), guided to the lesion, and specialized electrosurgical knives are used to dissect the tumor away from the underlying muscle layer.
For eligible early-stage cancers, ESD is widely considered equivalent or superior to surgery for local control, with lower procedural risk, shorter hospital stay, and faster return to normal life.
Bring your prior endoscopy images and biopsy reports
Korean hospitals can review your existing diagnostic files before your visit. Sending scanned reports and endoscopy photos to the international patient center in advance allows the endoscopist to assess eligibility and quote accurately — saving you a separate diagnostic consultation day in Korea.

Am I a Candidate?
ESD is appropriate for a defined set of patients and lesion types. A specialist endoscopist reviews imaging, prior biopsy, and endoscopic findings before recommending ESD.
Generally suitable candidates include:
- Early gastric cancer confined to the mucosa or with very shallow submucosal invasion
- Early colorectal or esophageal lesions that have not invaded the muscularis propria
- Lesions too large for conventional endoscopic mucosal resection (EMR) — typically >2 cm
- Patients who cannot tolerate general surgery due to comorbidities
- Recurrent polyps or lesions in areas where piecemeal removal would be incomplete
ESD may not be suitable when:
- The tumor has invaded deeply into the submucosal layer or beyond
- Imaging or biopsy suggests lymph node involvement
- The patient has severe bleeding disorders or cannot safely be sedated
- Lesion anatomy makes en bloc dissection technically unsafe
In Korea, most ESD candidates are identified through the national gastric cancer screening program, which uses endoscopy biennially for adults over 40. International patients typically arrive with prior biopsy results and endoscopic images, which Korean centers review before scheduling the procedure.
How the Procedure Works
On the day of the procedure, you fast for at least 6–8 hours. An intravenous line is placed, and sedation (or general anesthesia for complex cases) is administered.
The endoscopist inserts the flexible endoscope and navigates it to the lesion under direct visualization.
Step 1 — Marking: The borders of the lesion are marked using electrocautery dots placed around its perimeter.
Step 2 — Submucosal injection: A fluid solution (often containing a dye and epinephrine) is injected beneath the lesion. This lifts the tumor away from the muscularis layer, creating a safety cushion and reducing perforation risk.
Step 3 — Circumferential incision: A specialized ESD knife (e.g., insulation-tipped knife, hook knife, or flush knife) cuts a circular incision around the marked border.
Step 4 — Submucosal dissection: The endoscopist carefully dissects the connective tissue beneath the lesion, working across the submucosal plane. This step requires precision and is the most technically demanding phase — it is where Korea's high-volume expertise is most evident.
Step 5 — En bloc removal: The tumor is removed in one intact piece and retrieved for pathological analysis.
Step 6 — Wound closure: Any visible bleeding is treated with coagulation forceps. The resection site is inspected; hemostatic clips may be applied if needed.
Total procedure time is typically 1–3 hours, depending on lesion size and location.

Recovery Timeline
Recovery from ESD is considerably faster than open or laparoscopic surgery, but the resection wound inside the GI tract requires careful management.
Immediately after (Day 0–1): - You remain in recovery until sedation clears — typically 1–2 hours - Admission to a hospital room for monitoring; fasting continues overnight - Intravenous proton pump inhibitors (PPIs) are administered for gastric ESD to suppress acid and support healing
Days 1–3 (In hospital): - Clear liquids introduced when the endoscopist confirms no early bleeding or perforation - Transition to soft foods if tolerated - Most patients are discharged after 1–3 nights for gastric ESD; colorectal ESD may require 2–5 nights
Days 4–7 (Post-discharge, Korea stay recommended): - Soft, low-fiber diet — avoid spicy, acidic, and hard foods - Oral PPI medication continued (4–8 weeks for gastric cases) - Light activity only; no strenuous exercise - Return to desk work possible around Day 5 for many patients
Weeks 2–4: - Most patients gradually resume normal diet - Strenuous activity cleared at 2–4 weeks - A follow-up endoscopy is typically scheduled at 2–3 months to confirm complete healing and no residual lesion
Why staying 7–14 days in Korea matters: Pathology results take several days. An in-person follow-up with your Korean endoscopist before departure allows review of margins, discussion of surveillance schedule, and management of any early complications before you travel internationally.
Cost
Costs vary by hospital and case. Ask the hospital for a written, itemised estimate before you decide.
Why Korea
South Korea has emerged as one of the world's foremost destinations for ESD, for reasons that are structural, not merely reputational.
Volume-driven expertise. Korea has one of the world's highest rates of gastric cancer, and its national biennial screening program for adults over 40 has been running for decades. This combination produces a very high volume of early-detected lesions — creating consistent ESD caseloads at major hospitals.
High volume translates directly into endoscopist experience and refined technique.
Institutional training infrastructure. Major Seoul hospitals operate formal ESD training programs for both domestic and international physicians. This reflects the depth of Korea's expertise: Korea does not just perform ESD; it trains the world's endoscopists in it.
National outcomes data. Korea publishes national-level ESD statistics through its cancer registries and academic gastroenterology journals, providing transparency that supports evidence-based patient decisions. Published data from Korean registries have shaped international guidelines for ESD eligibility.
Medical tourism infrastructure. Seoul's Gangnam and Jongno districts are well-established medical tourism corridors. Seoul attracted approximately one million international medical visitors in 2024. Major hospitals maintain dedicated international patient centers with multilingual coordinators, translation, and care navigation.
Cost competitiveness. Medical procedures in Korea typically cost substantially less than in the United States or Western Europe, even in private-pay scenarios, without compromising equipment quality. Facilities in Seoul use current-generation endoscopy platforms and ESD knife technology.
Key Takeaways
- ESD removes early GI tumors en bloc through an endoscope — no incisions, faster recovery than surgery, and the intact specimen enables precise pathology.
- Korea's sustained high volume of early gastric cancer cases has produced deep, institutionalized ESD expertise, with major Seoul hospitals running international physician training programs.
- International patients should plan for 7–14 days in Korea to allow pathology review and a follow-up consult before flying home.
Frequently Asked Questions
Is ESD considered surgery?
ESD is classified as an advanced endoscopic procedure, not conventional surgery. No incisions are made in the abdomen. The endoscope is inserted through the mouth or anus, so there are no external wounds. However, it does require sedation or anesthesia and is performed in a hospital setting with the same post-procedure monitoring as a minor surgical case.
How do I know if I am a candidate for ESD rather than surgery?
Candidacy depends on lesion depth, size, location, and histology. In general, early-stage tumors confined to the mucosal or superficial submucosal layer without lymph node involvement are considered for ESD. Your Korean gastroenterologist will review prior biopsy results, CT or PET imaging, and may perform endoscopic ultrasound (EUS) to assess invasion depth before making a recommendation.
What is the difference between ESD and EMR (endoscopic mucosal resection)?
EMR removes the lesion by injecting fluid beneath it and snaring it off — it works well for smaller, flat polyps but often results in piecemeal removal for larger lesions. ESD uses electrosurgical knives to carefully dissect the submucosal layer and remove the lesion in one complete piece (en bloc), which enables more accurate pathological margin assessment and is preferred for larger or more complex lesions.
What are the main risks of ESD?
The two most common complications are bleeding and perforation of the GI wall. Bleeding can occur during the procedure or in the days after (delayed bleeding) and is usually managed endoscopically. Perforation risk is low in experienced hands and, if recognized promptly, is often managed with endoscopic clips rather than emergency surgery. Korea's high-volume centers have well-established protocols for managing both complications.
Will I need additional treatment after ESD?
If pathology confirms the lesion was removed with clear margins and no high-risk features (such as deep submucosal invasion or lymphovascular involvement), ESD alone is typically curative for early-stage tumors. If pathology shows concerning features, your Korean physician will discuss whether additional surgery or other treatment is needed. A surveillance endoscopy schedule is always recommended regardless of outcome.
How long should I plan to stay in Korea for ESD?
Most patients plan for 7–14 days. The procedure and immediate hospital stay account for 2–4 days. Remaining days allow for pathology results (typically 5–7 business days), a follow-up consultation to review findings, and safe discharge clearance before long-haul travel. Attempting to fly home immediately after discharge is not recommended.
Related Topics
Sources
International Patient Preparation Guides
Independent resources for international patients researching care in South Korea:
Bạn đang tìm hiểu về chăm sóc y tế tại Hàn Quốc?
KmedTour chỉ là nguồn thông tin. Hãy liên hệ trực tiếp với bệnh viện, hoặc tìm bệnh viện đã đăng ký tiếp nhận bệnh nhân nước ngoài trên cổng thông tin Medical Korea.
Quick Facts
Chi phí
Hãy yêu cầu bệnh viện báo giá bằng văn bản
Duration
3 days
Korean Hospitals
0+ Available
Bệnh viện có Endoscopic Submucosal Dissection
Medical Information Disclaimer
The information provided on this page about Endoscopic Submucosal Dissection is for general educational and informational purposes only. It is not intended as, and should not be construed as, medical advice, diagnosis, or treatment recommendations.
Always seek the advice of a qualified healthcare professional regarding any medical condition or treatment. Never disregard professional medical advice or delay seeking it because of information found on this website. Individual treatment outcomes may vary. Costs shown are estimates and may differ based on individual circumstances.
KmedTour is an independent information platform. It is not a medical provider or a registered foreign patient attraction agency, and it does not book treatment, take payment for treatment, or receive per-patient fees from hospitals. Treatment is arranged and paid for directly between you and the hospital.