Cancer
Laparoscopic Gastric Cancer Operation in Korea
Minimally invasive gastric cancer surgery in Korea — KLASS-validated technique, shorter recovery, and among the world's highest stomach cancer survival outcomes.
Quick Answer
- Laparoscopic gastrectomy removes the tumor and surrounding lymph nodes through small incisions, reducing blood loss and shortening recovery vs. open surgery.
- Korea's KLASS-01 and KLASS-02 trials helped establish laparoscopic distal gastrectomy as a globally recognized standard, now endorsed in NCCN guidelines.
- Korea's national gastric cancer screening program drives very high early-detection rates, creating exceptional surgical volume and specialization.
At a Glance
| Procedure time | 2–4 hours (varies by extent of resection) |
|---|---|
| Anesthesia | General anesthesia |
| Hospital stay | 7–12 days (Korean tertiary center average) |
| Recommended stay in Korea | 3–5 weeks (including pre-op evaluation and post-op follow-up) |
| Recovery | Return to light activity in 3–4 weeks; full recovery 6–10 weeks |
Overview
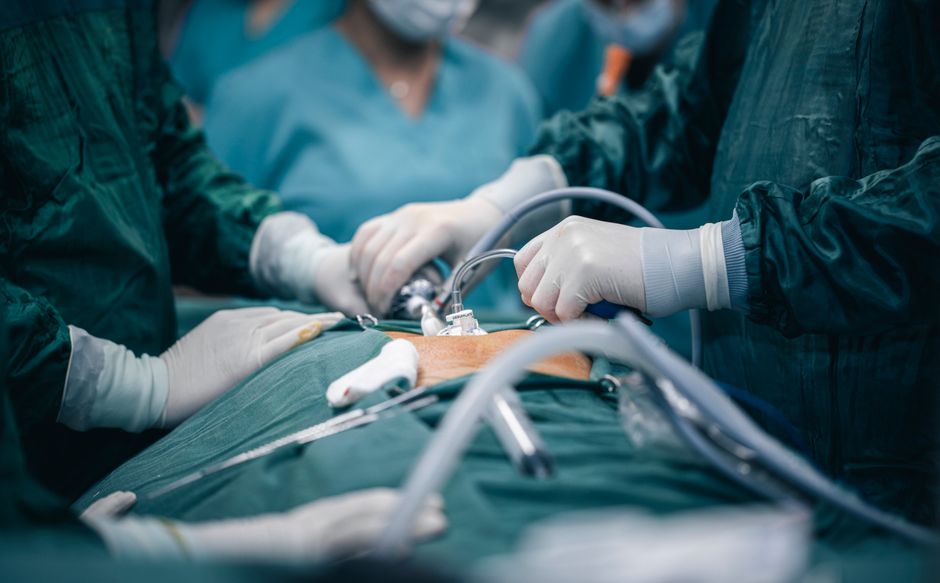
Laparoscopic gastrectomy for gastric cancer involves surgically removing part or all of the stomach — along with a defined margin of surrounding tissue and regional lymph nodes — using small keyhole incisions and a camera-guided instrument system.
The minimally invasive approach results in less intraoperative blood loss, reduced postoperative pain, and faster return to oral intake compared with traditional open surgery.
Korea has been at the forefront of refining this technique over the past two decades. Korean surgical teams, particularly at high-volume cancer centers in Seoul and Gangnam, routinely perform hundreds of laparoscopic gastrectomies per year, accumulating case volumes that are difficult to match outside East Asia.
The procedure encompasses two main approaches: distal gastrectomy (removing the lower portion of the stomach, most common for antral tumors) and total gastrectomy (removing the entire stomach, used for proximal or diffuse-type cancers).
Lymph node dissection — the D2 lymphadenectomy — is the Korean and Japanese standard and is associated with thorough staging and regional disease control.
Request an International Patient Center coordinator
Major Korean cancer hospitals in Seoul have dedicated international patient centers staffed with English-speaking medical coordinators. They can prepare itemized cost estimates, arrange visa support letters, and coordinate pre-op staging so you arrive with your workup largely complete — reducing your total time in Korea.

Am I a Candidate?
Candidacy for laparoscopic gastrectomy in Korea is determined by a multidisciplinary oncology team reviewing imaging, endoscopy, and pathology results.
Good candidates fit a clear profile. They typically have clinical stage I or II gastric adenocarcinoma (cT1–T3, limited nodal burden) or early gastric cancer (EGC) found on screening endoscopy, with no peritoneal seeding or distant metastasis on staging CT/PET.
They also need adequate cardiopulmonary reserve to tolerate general anesthesia and a BMI suitable for laparoscopic access, assessed per surgeon judgment.
Situations that may require open or alternative approaches: - T4b tumors invading adjacent structures - N2 bulky or matted lymphadenopathy - Prior abdominal surgery creating significant adhesions - Emergency presentation with perforation or hemorrhage
Korean guidelines (Korean Practice Guidelines for Gastric Cancer 2024) and NCCN both note that laparoscopic and robotic surgery are appropriate for EGC and selected advanced cases when performed by experienced surgeons. The treating team at the Korean center will confirm eligibility after reviewing all staging workup.
How the Procedure Works
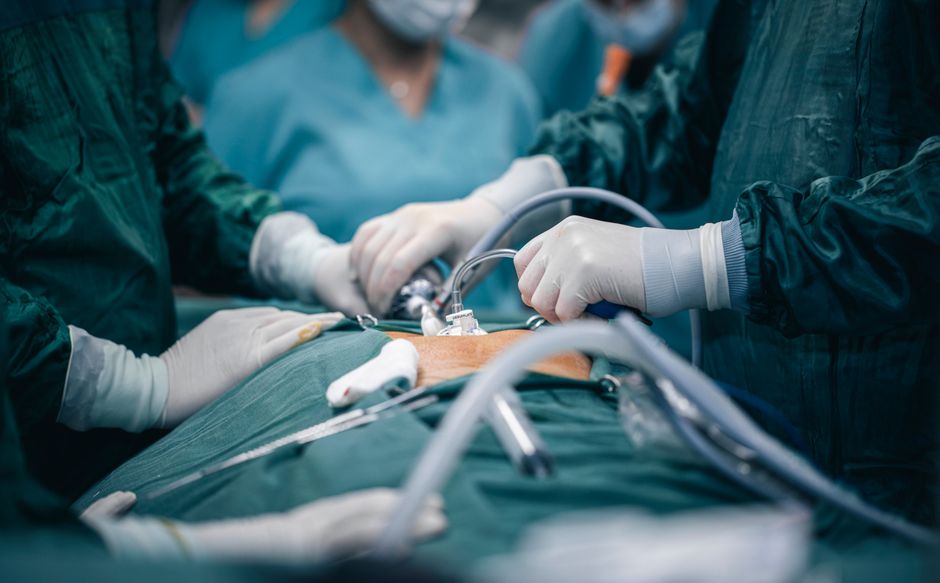
The surgical team begins with a general anesthetic induction. The abdomen is insufflated with carbon dioxide gas to create working space, and typically four to five small port incisions (each under 12 mm) are placed.
A high-definition laparoscope is inserted, and the surgeon uses articulated instruments to mobilize the stomach by dividing its ligamentous attachments and the blood supply systematically.
D2 lymphadenectomy — dissection of the regional lymph node stations around the celiac axis, left gastric artery, and hepatic artery — is performed concurrently. This is a defining feature of the Korean and Japanese approach and is considered oncologically superior to a limited (D1) dissection for most resectable gastric cancers.
The stomach is then divided at the planned resection margins using a laparoscopic stapler. For distal gastrectomy, a Billroth I, Billroth II, or Roux-en-Y reconstruction restores gastrointestinal continuity. For total gastrectomy, an esophagojejunostomy (Roux-en-Y) is fashioned.
A specimen retrieval bag is used to extract the resected tissue through a small extended incision. A drain is typically left near the anastomosis. Total operative time ranges from approximately 2 to 4 hours depending on resection extent and reconstruction type.
Recovery Timeline
Recovery from laparoscopic gastrectomy in Korea follows a structured enhanced recovery after surgery (ERAS) protocol at most major centers.
Days 1–3 (In hospital, early post-op): - Nasogastric tube removed within 24–48 hours if no leak - Clear liquids introduced around post-op day 2–3 - Ambulation encouraged from day 1 - Pain managed with epidural or IV analgesia transitioning to oral medications
Days 4–10 (In hospital, advancing diet): - Soft diet progression under dietitian supervision - Drain removed if output is low and non-bilious - Average Korean tertiary hospital discharge is approximately post-op day 8–10
Weeks 2–3 (Recovery accommodation in Korea): - Most international patients remain in Seoul or Gangnam for outpatient follow-up - Wound checks, blood tests, and surgical review - Diet counseling for post-gastrectomy nutrition (small frequent meals, B12 and iron monitoring)
Weeks 4–6 (Return home and light activity): - Light walking and household activity typically resumed - No heavy lifting or strenuous exercise
Weeks 6–10 (Full recovery): - Most patients return to normal daily activities - Oncology team determines whether adjuvant chemotherapy is indicated based on final pathology - Long-term nutritional supplementation (B12, iron, calcium) is common after total gastrectomy

Cost
Costs vary by hospital and case. Ask the hospital for a written, itemised estimate before you decide.
Why Korea
South Korea has one of the world's highest incidences of gastric cancer per capita, which has driven decades of specialized investment in surgical technique, screening infrastructure, and oncology research.
The country's National Cancer Screening Program for Gastric Cancer, launched in 1999 and expanded in 2002, means Korean surgeons routinely operate on early-stage disease — producing case volumes and surgical refinement that are rare globally.
The landmark KLASS (Korean Laparoscopic Gastrointestinal Surgery Study) trials — a series of multicenter prospective randomized controlled trials — generated the evidence base that led NCCN and other international guidelines to formally recognize laparoscopic distal gastrectomy as a standard treatment option for stage I gastric cancer.
Hospitals in Seoul and Gangnam with dedicated international patient centers offer English-language coordination, Korean-certified translators, and visa letter support — reducing logistical barriers for international patients traveling from abroad.
Cost is another practical factor: comparable procedures in the United States can cost three to five times more, while Korean hospitals maintain internationally comparable imaging, pathology, and intensive care infrastructure.
Key Takeaways
- Korea's KLASS trials produced the randomized evidence that placed laparoscopic gastrectomy in NCCN guidelines as a standard option for stage I gastric cancer.
- Korean tertiary centers achieve exceptional gastric cancer outcomes, linked to high surgical volume and a national early-detection screening program.
- A recommended stay of 3–5 weeks allows for pre-op evaluation, surgery, initial recovery, and at least one post-op surgical review before flying home.
Frequently Asked Questions
Is laparoscopic gastrectomy as effective as open surgery for gastric cancer?
For stage I gastric cancer, phase 3 randomized controlled trials (KLASS-01 in Korea, JCOG0912 in Japan) confirmed that laparoscopic distal gastrectomy is non-inferior to open surgery in oncological outcomes. NCCN guidelines now list it as a standard option. For more advanced stages, eligibility depends on tumor characteristics and is assessed by the surgical team.
How long do I need to stay in Korea after laparoscopic gastrectomy?
Most international patients plan a 3–5 week stay. Hospital discharge typically occurs around day 8–12 post-operatively, followed by 1–2 weeks of outpatient recovery and at least one surgical review visit before the medical team clears travel. Your specific timeline depends on recovery progress and whether any complications arise.
What is a D2 lymphadenectomy and why is it important?
D2 lymphadenectomy refers to systematic removal of the perigastric lymph nodes plus the nodes along the major arterial branches supplying the stomach (left gastric, common hepatic, celiac, and splenic arteries). Korean and Japanese surgical guidelines treat D2 dissection as the standard for resectable gastric cancer. It provides more thorough staging and is associated with better regional disease control than the more limited D1 dissection.
Will I need adjuvant chemotherapy after surgery in Korea?
Whether chemotherapy is recommended after surgery depends on the final pathological stage found in the resected specimen. Many patients with stage II or III disease receive adjuvant chemotherapy per Korean Practice Guidelines. The oncology team at the Korean center will discuss adjuvant options before you leave; ongoing chemotherapy is typically administered back in your home country with coordination between your Korean oncologist and local provider.
What nutritional changes are needed after gastrectomy?
After partial gastrectomy (distal), dietary adjustments include smaller, more frequent meals and avoiding high-sugar foods to prevent dumping syndrome. After total gastrectomy, lifelong supplementation with vitamin B12, iron, and calcium is typically required because these nutrients are absorbed in parts of the stomach and small intestine affected by surgery. Korean hospitals provide dietitian counseling during the inpatient stay.
Is robotic-assisted gastrectomy available in Korea and is it better?
Yes, robotic-assisted gastrectomy (typically da Vinci platform) is available at many Korean tertiary cancer centers. A 2025 systematic review found robotic gastrectomy to be non-inferior to laparoscopic gastrectomy in surgical outcomes with fewer postoperative complications in some analyses, but it involves longer operative time and higher cost. Your surgeon will advise whether robotic or standard laparoscopic approach is more appropriate for your case.
Related Topics
Sources
- Gastric cancer surgery in South Korea: Past, present, and future — PMC
- Costs and cost-effectiveness of robotic-assisted surgery in South Korea — Frontiers in Public Health 2025
- Performance of the National Cancer Screening Program for Gastric Cancer in Korea — PMC
- Enhanced recovery after surgery for laparoscopic gastrectomy in gastric cancer — PMC
- Recent status of laparoscopic distal gastrectomy in Korea: KLASS-07 multicenter cohort — PMC
International Patient Preparation Guides
Independent resources for international patients researching care in South Korea:
กำลังหาข้อมูลเกี่ยวกับการรักษาในเกาหลีอยู่หรือไม่?
KmedTour เป็นแหล่งข้อมูลเท่านั้น โปรดติดต่อโรงพยาบาลโดยตรง หรือค้นหาโรงพยาบาลที่ขึ้นทะเบียนรับผู้ป่วยต่างชาติได้ที่พอร์ทัล Medical Korea
Quick Facts
ค่าใช้จ่าย
ขอใบประเมินราคาเป็นลายลักษณ์อักษรจากโรงพยาบาล
Duration
14 days
Korean Hospitals
0+ Available
โรงพยาบาลที่มี Laparoscopic Gastric Cancer Operation
Medical Information Disclaimer
The information provided on this page about Laparoscopic Gastric Cancer Operation is for general educational and informational purposes only. It is not intended as, and should not be construed as, medical advice, diagnosis, or treatment recommendations.
Always seek the advice of a qualified healthcare professional regarding any medical condition or treatment. Never disregard professional medical advice or delay seeking it because of information found on this website. Individual treatment outcomes may vary. Costs shown are estimates and may differ based on individual circumstances.
KmedTour is an independent information platform. It is not a medical provider or a registered foreign patient attraction agency, and it does not book treatment, take payment for treatment, or receive per-patient fees from hospitals. Treatment is arranged and paid for directly between you and the hospital.