
Cancer
Endoscopic Thyroidectomy in Korea
Scarless thyroid removal in South Korea using remote-access endoscopic techniques pioneered at Seoul teaching hospitals.
Quick Answer
- Endoscopic thyroidectomy removes part or all of the thyroid through small incisions hidden in the armpit, chest, or oral vestibule — no neck scar.
- South Korea pioneered several key techniques, including the gasless transaxillary approach and the bilateral axillo-breast approach (BABA), widely used at high-volume Korean centers.
- Most patients are discharged within 1–3 nights and can fly home after approximately 10–14 days of local recovery.
At a Glance
| Procedure time | 90–180 minutes (varies by technique and gland volume) |
|---|---|
| Anesthesia | General anesthesia |
| Hospital stay | 1–3 nights |
| Recommended stay in Korea | 10–14 days (includes post-op check and pathology review) |
| Recovery | Return to light activity in 1–2 weeks; full recovery 3–6 weeks |
Overview
Endoscopic thyroidectomy is a minimally invasive surgical approach that removes thyroid tissue without placing an incision on the neck.
Instead, surgeons work through small ports located in the armpit, the chest wall, or the oral vestibule — sites where scars are either hidden or completely absent. A thin camera (endoscope) transmits a magnified view of the operative field, guiding precision dissection around the thyroid gland.
Korea has been one of the world's primary centers developing and refining these techniques since the early 2000s. The gasless transaxillary approach and the bilateral axillo-breast approach (BABA) — both refined at major Seoul teaching hospitals — account for the majority of endoscopic thyroid procedures performed domestically.
The newer transoral endoscopic thyroidectomy vestibular approach (TOETVA) leaves zero external scars by entering entirely through the inner lower lip.
Because Korean surgeons perform these procedures at high volume, operative teams are experienced in managing the delicate anatomy around the recurrent laryngeal nerve and parathyroid glands, which are the key safety considerations in any thyroid surgery.
Request pathology turnaround time before booking
Final pathology results from thyroid surgery typically take 5–10 business days in Korea. Build this window into your stay so your surgeon can review findings before you depart — this is particularly important if cancer is suspected or confirmed.

Am I a Candidate?
Endoscopic thyroidectomy is not appropriate for every thyroid patient. Surgeons evaluate each case individually before recommending a remote-access approach.
Several groups qualify. Typical candidates have benign thyroid nodules or cysts (commonly ≤ 4–5 cm), well-differentiated low-risk papillary thyroid microcarcinoma (often ≤ 1 cm, single lesion), or hyperthyroidism (Graves' disease or toxic nodular goiter) when size permits.
Mild-to-moderate thyroid enlargement without retrosternal extension also qualifies, as does a strong preference to avoid a visible neck scar.
The approach is generally not recommended for: - Large goiters with significant retrosternal component - Aggressive or widely invasive thyroid cancers - Prior neck surgery or radiation causing extensive adhesions - Patients with certain body habitus or chest-wall characteristics that limit port placement
A pre-operative ultrasound and, in cancer cases, fine-needle aspiration cytology (FNAC) are standard requirements. Hormone panels and laryngoscopy to assess vocal-cord function are also routine before surgery.
How the Procedure Works
The specific steps differ by technique, but the general sequence is similar across all remote-access endoscopic approaches.
Pre-operative preparation The patient is admitted the evening before or on the morning of surgery. Blood work, anaesthesia assessment, and a final imaging review take place. The neck and access site (axilla, chest, or oral vestibule) are prepared and marked.
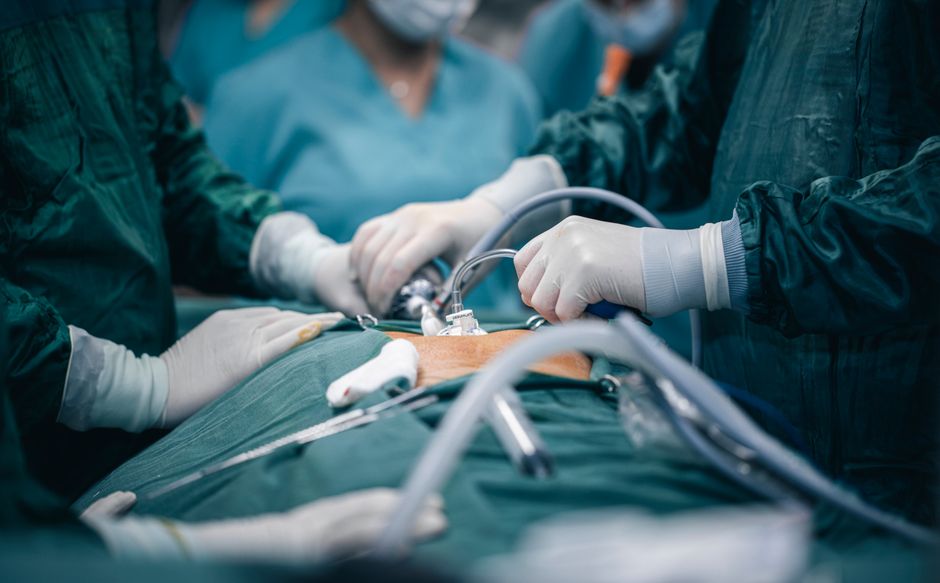
Port placement Under general anaesthesia, 3–4 small incisions (typically 5–12 mm each) are made at the chosen access site. Trocars or retractors are introduced to create a working corridor through the subcutaneous tissue toward the thyroid.
For the gasless transaxillary approach, a dedicated retractor system holds the space open mechanically without gas insufflation.
Dissection and gland removal The endoscope is inserted, providing a high-definition view. Surgeons carefully dissect around the thyroid, identifying and preserving the recurrent laryngeal nerve and parathyroid glands. The thyroid lobe — or the entire gland for total thyroidectomy — is freed and extracted through one of the port sites.
Closure Small access incisions are closed with absorbable sutures or skin adhesive. A drain may be placed for 12–24 hours. The patient moves to a monitored recovery room.
Recovery Timeline
Recovery after endoscopic thyroidectomy follows a predictable progression, though individual timelines vary by technique and whether a partial or total thyroidectomy was performed.
Days 1–2 (Hospital) Pain at the access site and mild throat soreness are common. Voice may be slightly hoarse — this usually resolves within days. The care team monitors calcium levels closely, particularly after total thyroidectomy, as temporary parathyroid disturbance is possible.
Days 3–7 (Early outpatient) Most patients are discharged by day 3. Light walking is encouraged. Swallowing soft foods is typically comfortable. Activity near the port site (e.g., raising the arm forcefully for transaxillary patients) is limited.
Days 7–14 (Pre-departure assessment) - Follow-up clinic visit to review pathology and wound healing - Thyroid hormone replacement initiated if indicated (total thyroidectomy patients require lifelong levothyroxine) - Calcium and parathyroid hormone levels confirmed stable - Clearance for air travel
Weeks 3–6 (Full recovery) Return to desk work: approximately 1–2 weeks. Physical work or exercise: 3–6 weeks. Final scar maturation at the port sites takes 3–6 months.
Cost
Costs vary by hospital and case. Ask the hospital for a written, itemised estimate before you decide.
Why Korea
South Korea has developed one of the world's highest concentrations of endoscopic thyroid surgical expertise, driven by a combination of patient demand, institutional research, and government-supported medical tourism infrastructure.
Technique innovation Several of the most widely adopted remote-access thyroid techniques — including the BABA approach — were pioneered and refined at Korean teaching hospitals, particularly in Seoul. Korean surgical teams published benchmark multicenter data that informed international training programs.
Volume and experience High annual case volumes at major centers mean surgical teams — including scrub nurses, anaesthetists, and coordinators — work together repeatedly on the same procedures. Volume is one of the most consistently cited drivers of surgical safety outcomes.
Regulatory framework Korea's Ministry of Food and Drug Safety (MFDS) regulates medical devices and pharmaceuticals used in procedures. Hospitals serving international patients must register with authorities and carry mandatory malpractice liability insurance under national law.
The Korea Health Industry Development Institute (KHIDI) and the Medical Korea initiative coordinate government-backed support for inbound medical travelers, including patient advocacy and dispute resolution services.
Seoul and Gangnam access Gangnam-gu, Seoul — home to a dense cluster of specialist clinics and tertiary hospitals — offers direct metro and taxi access from Incheon International Airport (ICN). Major university-affiliated hospitals in Seoul maintain dedicated international patient centers with multilingual coordinators.
Cost competitiveness Korean pricing is substantially below US and UK benchmarks for equivalent procedures, without the quality trade-off that often accompanies low-cost destinations.
Key Takeaways
- South Korea is a globally recognized center for endoscopic thyroid surgery, having developed and exported techniques like the BABA and gasless transaxillary approach.
- No visible neck scar is the primary cosmetic advantage; technique choice (transaxillary, BABA, or transoral) depends on anatomy, diagnosis, and surgeon expertise.
- Plan a minimum 10–14 day stay to allow safe post-operative monitoring, pathology review, and medical clearance before flying home.
Frequently Asked Questions
Will I have any visible scar after endoscopic thyroidectomy?
That depends on the technique. The gasless transaxillary approach leaves a small scar in the armpit crease, which is hidden when the arm rests at the side. The BABA approach places incisions in the axillae and around the areolae. The transoral vestibular approach (TOETVA) leaves no external scar at all.
Is endoscopic thyroidectomy safe for thyroid cancer?
It is performed for selected low-risk, well-differentiated thyroid cancers — typically small papillary carcinomas confirmed by pre-operative imaging and biopsy to be confined to the gland without lymph node involvement. It is not appropriate for aggressive histologies or cancers with confirmed spread. Your oncology and surgical team will determine eligibility based on your specific staging.
How long will I need to take thyroid hormone medication after surgery?
If you have a total thyroidectomy (removal of the entire gland), you will require lifelong levothyroxine (synthetic thyroid hormone) replacement. After a hemithyroidectomy (one lobe removed), many patients retain sufficient hormone production from the remaining lobe, though some will eventually need supplementation. Your endocrinologist will monitor TSH levels post-operatively to guide this.
What is the difference between the BABA and transaxillary approaches?
Both avoid a neck incision. The BABA (bilateral axillo-breast approach) uses four small ports — two in the axillae and two near the areolae — and provides a straight-on midline view of the thyroid similar to open surgery, which can make it preferable for total thyroidectomy or bilateral disease. Korean centers have high experience with both.
Will I experience voice changes after the operation?
Temporary hoarseness or voice fatigue is relatively common in the first days after any thyroid surgery and usually resolves within a few weeks as swelling subsides. Permanent voice change from recurrent laryngeal nerve injury is an uncommon but recognized risk of thyroid surgery by any technique. A laryngoscopy check before and after surgery is routine at experienced Korean centers.
Can I travel to Korea alone for this procedure?
While it is possible, most patients benefit from a companion for at least the first few post-operative days — particularly if communication in Korean is limited. Korean hospitals with registered international patient services provide multilingual medical coordinators who assist with translation, scheduling, and logistics. The Medical Korea initiative also offers guidance on finding vetted registered facilities for overseas patients.
Related Topics
Sources
- Endoscopic Thyroidectomy for Differentiated Thyroid Cancer — PMC/NIH
- Nationwide multicenter survey for current status of endoscopic thyroidectomy in Korea — PubMed
- Comparison between gas insufflation and gasless techniques for endoscopic transaxillary thyroidectomy — PMC/NIH
- Medical Korea — Official International Patient Portal
International Patient Preparation Guides
Independent resources for international patients researching care in South Korea:
Unatafiti huduma nchini Korea?
KmedTour ni chanzo cha taarifa tu. Wasiliana na hospitali moja kwa moja, au tafuta hospitali iliyosajiliwa kutibu wagonjwa wa kigeni kwenye tovuti ya Medical Korea.
Quick Facts
Gharama
Omba makadirio ya maandishi kutoka hospitali
Duration
5 days
Korean Hospitals
0+ Available
Hospitali zinazotoa Endoscopic Thyroidectomy
Medical Information Disclaimer
The information provided on this page about Endoscopic Thyroidectomy is for general educational and informational purposes only. It is not intended as, and should not be construed as, medical advice, diagnosis, or treatment recommendations.
Always seek the advice of a qualified healthcare professional regarding any medical condition or treatment. Never disregard professional medical advice or delay seeking it because of information found on this website. Individual treatment outcomes may vary. Costs shown are estimates and may differ based on individual circumstances.
KmedTour is an independent information platform. It is not a medical provider or a registered foreign patient attraction agency, and it does not book treatment, take payment for treatment, or receive per-patient fees from hospitals. Treatment is arranged and paid for directly between you and the hospital.