Transplantation
Dual Donor Liver Transplantation in Korea
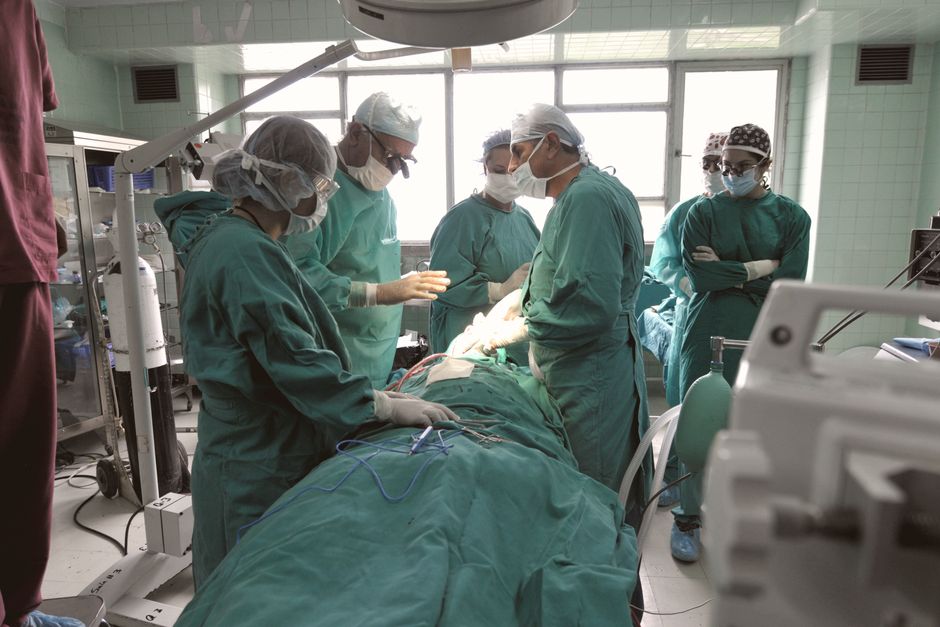
Korea pioneered dual-donor LDLT: two living donors each contribute a partial liver segment to one recipient.
Quick Answer
- Two living donors, each donating a partial lobe, together provide a combined graft large enough for one adult recipient — eliminating the small-for-size problem that limits single-donor LDLT.
- Korea performed the world's first dual living donor liver transplantation in March 2000 at a Seoul tertiary center, and Korean surgeons continue to lead global volume and refinement of the technique.
- pricing.
- Total time in Korea is typically 8–12 weeks, covering pre-operative evaluation, surgery, ICU, ward recovery, and mandatory outpatient follow-up before international travel is cleared.
At a Glance
| Procedure time | 14–20 hours (recipient); 4–6 hours per donor (sequential) |
|---|---|
| Anesthesia | General anesthesia for all three patients |
| Hospital stay | Recipient: 3–5 days ICU, then 2–3 weeks on ward; each donor: 7–10 days |
| Recommended stay in Korea | 8–12 weeks total (evaluation through outpatient clearance) |
| Recovery | Return to light activity: 3–4 months; full recovery: 6–12 months |
Overview
Dual-donor living donor liver transplantation (DD-LDLT) is a surgical solution developed when a single living donor cannot safely provide a graft large enough for an adult recipient.
In standard living donor liver transplantation, the donor gives either a right or left lobe. If the donor's liver is too small — or if donating the required volume would leave the donor with an unsafe remnant — the transplant cannot proceed.
DD-LDLT resolves this by recruiting two separate living donors. Each donor undergoes a partial hepatectomy, typically donating either two left-lobe or left-lateral-segment grafts, or one right lobe and one left lobe. The two grafts are implanted together into the recipient, whose native liver has been removed.
The combined graft volume meets the recipient's metabolic needs while each individual donor retains a safe remnant liver.
Korea pioneered this technique in 2000 and has accumulated the world's largest institutional experience. Published outcomes show that long-term recipient survival in DD-LDLT is comparable to conventional single-donor LDLT when performed at high-volume centers.
The procedure is technically demanding — operative time for the recipient surgery alone typically ranges from 14 to 20 hours — and is offered only at specialized hepatobiliary units with dedicated transplant teams and high-dependency infrastructure.
Three independent consents required
Korean transplant centers require each donor to give informed consent independently — without the recipient or other donor present — and to undergo a separate psychological evaluation confirming voluntary participation. Families coordinating multiple donors should allow extra lead time for the ethics and pre-operative evaluation process.

Am I a Candidate?
DD-LDLT is considered when all three of the following conditions apply: the recipient has end-stage liver disease or hepatocellular carcinoma within accepted transplant criteria; a single living donor is available but cannot safely provide adequate graft volume; and two willing, medically suitable donors exist.
Typical recipient indications include:
- Liver cirrhosis (viral, alcoholic, autoimmune, or metabolic origin)
- Hepatocellular carcinoma meeting transplant criteria
- Acute-on-chronic liver failure requiring urgent transplant
- Metabolic liver disease causing systemic complications
Each prospective donor undergoes extensive independent evaluation:
- Volumetric CT to confirm adequate remnant liver after planned resection
- Full blood-group and cross-match compatibility workup
- Psychological assessment to confirm voluntary, informed consent
- Cardiopulmonary fitness screening
Candidates are excluded if either donor's remnant would fall below safe thresholds, if the recipient has uncontrolled systemic infection, or if extrahepatic malignancy is present.
Because three people undergo major surgery in the same operative window, the ethics review and multidisciplinary case conference requirements are more rigorous than for standard LDLT. Korean transplant centers have established institutional protocols for this review process.
How the Procedure Works
Pre-operative preparation spans several weeks. The recipient, donor A, and donor B each complete independent work-ups. Volumetric imaging maps each donor's anatomy; the surgical team plans resection planes and graft implantation sequence before any incisions are made.
On the day of surgery, the two donor hepatectomies typically proceed sequentially or in parallel in adjacent theatres, timed so both grafts are ready for back-table preparation before recipient hepatectomy is completed.
Donor surgery (each donor):
- General anesthesia; laparoscopic-assisted or open approach depending on anatomy
- Careful dissection and division of the designated hepatic lobe or segment
- Bile duct and vascular pedicle division with meticulous hemostasis
- Graft flushed and placed on ice; donor abdomen closed
Recipient surgery:
- Diseased native liver removed (total hepatectomy)
- Vascular reconstruction for each graft: portal vein, hepatic artery, hepatic vein anastomoses performed in sequence
- Both grafts positioned in the abdominal cavity — typically one in the right anatomical position, one in the left, or both in a modified configuration
- Biliary reconstruction (hepaticojejunostomy or duct-to-duct) for each graft
- Abdominal closure with drains in situ
Post-operatively, the recipient is transferred to ICU. Immunosuppression begins immediately. Each graft is monitored with daily liver-function tests and Doppler ultrasound to confirm vascular patency and graft regeneration.
Recovery Timeline
ICU phase (days 1–5): The recipient is closely monitored for primary graft function, vascular complications, and bleeding. Each donor is also monitored in a high-dependency setting for the first 24–48 hours.
Ward phase (weeks 1–4): Once haemodynamically stable, the recipient transfers to the transplant ward. Liver enzymes, bilirubin, and coagulation are tracked daily, then every few days. Oral immunosuppressants are titrated. Physical therapy begins gently.
- Donors are typically discharged within 7–10 days if recovery is uncomplicated
- Recipients remain in-hospital for 2–3 weeks on average; longer if rejection or biliary complications require intervention
Outpatient phase in Korea (weeks 4–12): After hospital discharge, the recipient attends outpatient clinic two to three times per week initially, then weekly. Tacrolimus or cyclosporine trough levels are monitored closely. Liver biopsy may be performed if rejection is suspected.
International patients are cleared to fly home only after the transplant team confirms stable graft function, no active complications, and an established immunosuppression regimen the local team can manage.
Long-term recovery:
- Light activity resumes around months 3–4
- Return to desk work: approximately 3–6 months
- Full physical recovery and stabilised immunosuppression: 6–12 months
- Lifelong immunosuppression and annual follow-up are required

Cost
Costs vary by hospital and case. Ask the hospital for a written, itemised estimate before you decide.
Why Korea
Korea performed the world's first dual living donor liver transplantation in March 2000, a landmark that established the country as the global pioneer of this technique.
In the decades since, Korean hepatobiliary teams have refined donor selection criteria, graft combination strategies, and vascular reconstruction sequences to a degree unmatched outside East Asia.
Korea has the highest rate of living donor liver transplantation per capita in the world, according to IRODaT data. This volume translates directly into surgical precision: scrub nurses, anesthesiologists, perfusionists, and hepatologists work together in teams that perform multiple LDLT cases each week, not each year.
Several structural advantages reinforce Korea's position:
- Tertiary-center infrastructure: Seoul's major transplant hospitals operate dedicated hepatobiliary ICUs, on-site pathology for rapid frozen sections, and 24-hour vascular surgery backup — all essential when three simultaneous major surgeries are involved
- Regulatory framework: The Korean Health Industry Development Institute (KHIDI) and the Medical Korea program actively support inbound medical tourism with standardized quality audits and international patient coordinators
- Published evidence base: Korean surgeons have authored much of the peer-reviewed literature on dual-graft outcomes, graft regeneration kinetics, and ABO-incompatible dual-graft protocols
- Cost efficiency: Korea achieves outcomes comparable to top Western centers at 20–30% of the equivalent U.S. price, without compromising on implant quality, ICU standards, or nursing ratios
For patients who cannot access a deceased-donor liver in their home country and lack a single donor with sufficient liver volume, Korea's DD-LDLT program represents one of the few viable options in the world.
Key Takeaways
- DD-LDLT uses two living donors whose partial grafts are combined to meet one adult recipient's needs — Korea pioneered the technique in 2000 and leads global volume.
- pricing.
- Recipient hospital stay averages 3–4 weeks; each donor is typically discharged within 7–10 days; international patients should budget 8–12 weeks in Korea before flying home.
- Lifelong immunosuppression and regular liver-function monitoring are required after transplant — coordinate with a hepatologist in your home country before travel.
- Only a small number of centers worldwide perform this procedure routinely; volume and institutional experience are the most important factors when selecting a hospital.
Frequently Asked Questions
Why does dual-donor liver transplant require two donors instead of one?
When a single donor's liver is too small relative to the recipient's body size — or when safely donating the required volume would leave the donor with insufficient remnant liver — a single donation is not feasible. Recruiting a second donor allows both partial grafts to be combined, meeting the recipient's metabolic needs while keeping each donor's residual liver above safe thresholds.
Are both donors operated on the same day as the recipient?
Yes. To minimize cold ischemia time (the period the graft spends without blood supply), the two donor hepatectomies are scheduled on the same day as the recipient surgery, typically sequenced so both grafts complete back-table preparation just as the recipient hepatectomy finishes. This requires coordinating three operating theatres and teams simultaneously.
What is the long-term graft survival rate for dual-donor LDLT compared to standard LDLT?
Published peer-reviewed studies indicate that long-term recipient survival in dual-donor LDLT is comparable to conventional single-donor LDLT when performed at experienced high-volume centers. The early post-operative period carries somewhat higher surgical complexity, but graft outcomes normalize over time as both partial livers regenerate and function as a single organ unit.
Can the two living donors be blood-type incompatible with the recipient?
Korean centers have published experience with ABO-incompatible dual-graft protocols — situations where one or both donors do not share the recipient's blood type. These cases require additional desensitization treatment (plasmapheresis, rituximab) and carry additional risk and cost. Compatibility is strongly preferred and is evaluated during the pre-operative workup.
How long does each donor need to recover before returning to work?
Each donor typically spends 7–10 days in hospital. Most donors can return to desk work within 4–6 weeks of surgery. Physically demanding jobs may require 2–3 months off. Long-term liver function in carefully selected donors is generally preserved, as the remnant liver regenerates significantly within the first 3 months.
Does the Medical Korea program support international patients seeking dual-donor LDLT?
The Medical Korea program, administered through KHIDI and the Ministry of Health and Welfare, provides information on accredited transplant facilities and offers international patient support services. International patients should contact the international patient department of their chosen center directly, as transplant cases require individualized assessment that cannot be handled through a general tourism portal alone.
Related Topics
Sources
- Living donor liver transplantation using dual grafts from two donors — PubMed
- Dual-graft adult living donor liver transplantation — PubMed
- Regeneration and outcome of dual grafts in living donor liver transplantation — PubMed
- Current status and outcome of liver transplantation in South Korea — PMC
- Medical Korea — Transplantation (official government portal)
International Patient Preparation Guides
Independent resources for international patients researching care in South Korea:
Sedang mengkaji penjagaan di Korea?
KmedTour hanyalah sumber maklumat. Hubungi hospital secara terus, atau cari hospital yang berdaftar untuk merawat pesakit asing di portal Medical Korea.
Quick Facts
Kos
Minta anggaran bertulis daripada hospital
Duration
21 days
Korean Hospitals
0+ Available
Hospital yang menawarkan Dual Donor Liver Transplantation
Medical Information Disclaimer
The information provided on this page about Dual Donor Liver Transplantation is for general educational and informational purposes only. It is not intended as, and should not be construed as, medical advice, diagnosis, or treatment recommendations.
Always seek the advice of a qualified healthcare professional regarding any medical condition or treatment. Never disregard professional medical advice or delay seeking it because of information found on this website. Individual treatment outcomes may vary. Costs shown are estimates and may differ based on individual circumstances.
KmedTour is an independent information platform. It is not a medical provider or a registered foreign patient attraction agency, and it does not book treatment, take payment for treatment, or receive per-patient fees from hospitals. Treatment is arranged and paid for directly between you and the hospital.