Transplantation
Cornea Transplantation in Korea
Cornea transplant surgery in South Korea using PK, DSAEK, or DMEK techniques — internationally competitive costs and advanced ophthalmology centers.
Quick Answer
- Full-thickness (penetrating keratoplasty) and lamellar procedures (DSAEK, DMEK) are all available at major Korean eye centers, with surgeons selecting technique based on which corneal layer is diseased.
- Recovery varies by technique: DSAEK/DMEK patients typically see meaningful improvement in weeks to months, while full-thickness PK grafts take 12–24 months to reach stable vision.
- Korea benefits from an active Korean Ophthalmological Society data-sharing network and ties to international eye banks (including Eversight) to supplement domestic cornea supply.
At a Glance
| Procedure time | 1–2 hours (varies by technique) |
|---|---|
| Anesthesia | Local with sedation (most cases); general anesthesia available |
| Hospital stay | Same-day or 1 night |
| Recommended stay in Korea | 3–4 weeks minimum for initial post-op monitoring |
| Recovery | DSAEK/DMEK: vision stabilizes over weeks to months; PK: up to 12–24 months for stable vision |
Overview
The cornea is the clear outer dome of the eye. When it becomes permanently clouded by disease, injury, or dystrophy, a corneal transplant — or keratoplasty — replaces the damaged tissue with healthy donor tissue to restore transparency and vision.
Surgeons in Korea work across three main surgical categories. Penetrating keratoplasty (PK or PKP) is the traditional full-thickness approach, replacing all five corneal layers in a single disc-shaped graft. It remains indicated when disease affects the entire cornea.
Anterior lamellar keratoplasty (ALK/DALK) replaces the front layers of the cornea while preserving the patient's own healthy endothelium, reducing rejection risk compared to full-thickness grafts.
Posterior lamellar procedures — DSAEK and DMEK — target only the innermost endothelial layer. DSAEK (Descemet Stripping Automated Endothelial Keratoplasty) delivers a thin tissue disc; DMEK (Descemet Membrane Endothelial Keratoplasty) goes thinner still, transplanting just the Descemet membrane and its endothelial cells.
Both posterior techniques offer faster rehabilitation and less surgically-induced astigmatism than full-thickness PK.
Korean ophthalmologists track and publish transplant volume and outcomes through the Korean Ophthalmological Society (KOS), and a published 2021–2023 analysis integrating KOS and Eversight Eye Bank data documents current surgical trends and donor demographics in the country.
This infrastructure of data-driven practice underpins the quality of care available to international patients.
Book a pre-travel teleconsultation
Most major Korean eye centers offer a remote consultation where you can submit corneal topography and specular microscopy results from your home country. This allows the surgical team to select the appropriate technique — PK vs DSAEK vs DMEK — before you book flights, reducing the risk of unexpected changes to your plan or budget on arrival.
Plan your 3–4 week minimum stay
Korean post-operative protocols for corneal transplant require in-person follow-up at roughly Day 1, Week 1, and Week 3–4. DMEK patients in particular must be assessed for graft attachment before the air bubble fully absorbs. Do not plan to fly home within the first two weeks.
Am I a Candidate?
Not every patient with impaired vision is a candidate for corneal transplant. A thorough pre-operative evaluation at a Korean eye center will assess several factors before a technique is recommended.
Conditions that commonly lead to a transplant referral include:
- Keratoconus — progressive thinning and cone-shaped distortion of the cornea
- Fuchs' endothelial dystrophy — inherited degeneration of the corneal endothelium causing swelling and cloudiness
- Bullous keratopathy — painful corneal swelling often following cataract or glaucoma surgery
- Corneal scarring from prior infection (e.g., herpes simplex keratitis, bacterial ulcers), trauma, or chemical injury
- Failed previous corneal graft requiring re-transplantation
- Corneal stromal dystrophies affecting front layers
Patients are generally NOT candidates if active ocular infection is present, if the underlying cause of vision loss originates behind the cornea (retina, optic nerve), or if systemic health makes surgery unsafe. Moderate-to-severe dry eye and uncontrolled glaucoma require treatment before proceeding.
Pre-op workup typically includes corneal topography, specular microscopy (endothelial cell count), anterior segment OCT, and a full assessment of intraocular pressure. Patients should disclose all medications — particularly immunosuppressants — as these affect rejection risk management.
How the Procedure Works
Surgery follows a clearly defined sequence, though it differs meaningfully between full-thickness and lamellar approaches.
Penetrating keratoplasty (PK)
The surgeon uses a trephine — a circular cutting instrument — to remove a precisely sized disc of the patient's full-thickness cornea. A matched donor disc, typically 7.5–8.5 mm in diameter, is sutured into place using 16–24 fine interrupted or running sutures.
The eye is patched, and sutures remain in place for up to 12–24 months while healing progresses.
DSAEK
The diseased endothelium is stripped. A thin donor disc (roughly 100–150 microns) is folded, inserted through a small incision, and unfolded against the patient's corneal stroma using an air bubble. No sutures penetrate the graft itself. The compactness of the incision reduces astigmatism induction substantially compared to PK.
DMEK
Only the Descemet membrane and its attached endothelial cell monolayer — roughly 10–15 microns thick — are transplanted. The tissue is rolled into a scroll, delivered through a small corneal incision, and unrolled in the anterior chamber with careful fluid maneuvering and air.
DMEK demands significant surgical precision but, when successful, produces the closest approximation to a native endothelium and the fastest visual rehabilitation.
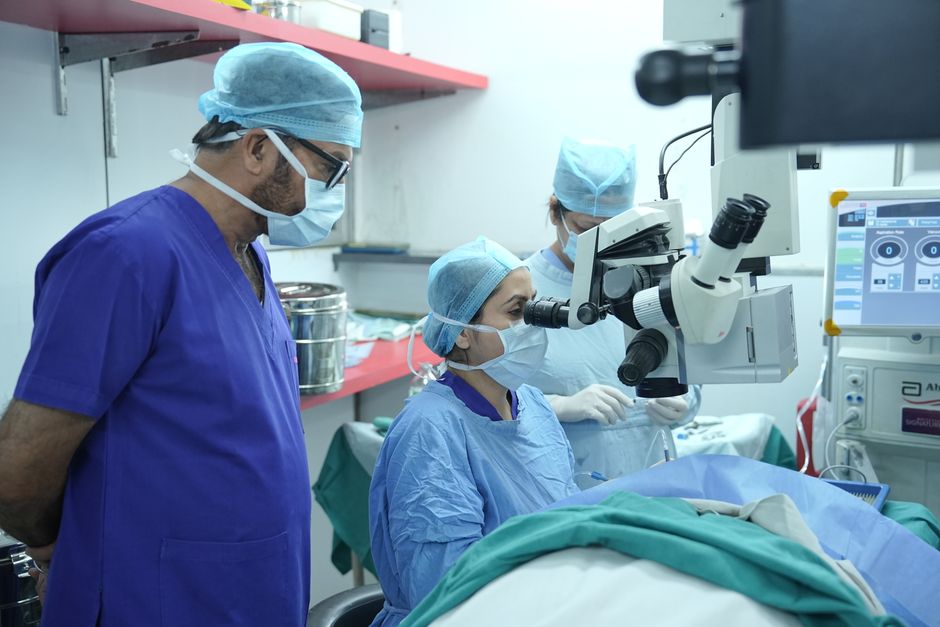
All three approaches are performed under sterile conditions in an ophthalmic operating theater, typically under local anesthesia with sedation. Procedure duration is generally one to two hours.
Recovery Timeline
The post-operative path differs considerably depending on which technique was used.
Immediate (Days 1–7)
Patients rest with the operated eye patched. DSAEK and DMEK patients may need to maintain a specific head position (face up) for hours post-op to keep the air bubble pressing the graft into place. Antibiotic and steroid eye drops begin immediately and continue for months.
Early recovery (Weeks 1–4)
Vision is blurry but light sensitivity diminishes. Korean programs typically require patients to remain in-country for a minimum of two to four weeks to attend critical follow-up visits, confirm graft attachment (especially for DMEK), and manage any early complications such as graft detachment or elevated intraocular pressure.
Mid-term (Months 1–6)
- DSAEK/DMEK: functional vision often improves within six to twelve weeks; most stabilization occurs by three to six months
- PK: sutures remain in place; vision fluctuates with refractive change; suture adjustment may be needed
Long-term (Months 6–24)
For PK grafts, sutures are removed selectively between 12 and 24 months. Final refraction — glasses or contact lenses — is prescribed after suture removal. Patients are monitored long-term for rejection (sudden redness, light sensitivity, decreased vision) as rejection can occur years after surgery and requires prompt steroid treatment.
Physical restrictions during healing include avoiding heavy lifting, contact sports, and swimming. Driving timelines depend on visual acuity recovery.
Cost
Costs vary by hospital and case. Ask the hospital for a written, itemised estimate before you decide.
Why Korea
South Korea has developed one of Asia's most capable corneal transplant programs, shaped by several converging factors.
Ophthalmological infrastructure
Seoul, particularly the Gangnam and Jongno districts, hosts internationally recognized tertiary eye centers operating within university medical systems. These hospitals run dedicated cornea services with subspecialty-trained surgeons who perform the full range of procedures — PK, DALK, DSAEK, DMEK — rather than routing different technique types to different facilities.
Regulatory and accreditation framework
The Ministry of Food and Drug Safety (MFDS) regulates tissue banking and donor cornea standards in Korea. The Korea Health Industry Development Institute (KHIDI) supports the Medical Korea portal, the government's official medical tourism gateway, which lists verified hospitals and coordinates international patient services.
Foreign patients using MFDS-regulated tissue and KHIDI-listed hospitals have recourse to standardized safety oversight.
International tissue partnerships
Domestic cornea supply in Korea faces the same donation-shortage challenges seen across Asia. To bridge the gap, major Korean centers have established partnerships with international eye banks — including US-based Eversight — for tissue procurement.
A 2021–2023 analysis published by Korean researchers integrates both domestic KOS survey data and Eversight supply data, reflecting how systematically this gap is managed rather than left to improvisation.
Data-driven practice
The Korean Ophthalmological Society maintains national transplant registries and publishes outcome data, enabling surgeons to benchmark results against peer institutions. This culture of transparent outcome tracking benefits international patients who wish to evaluate quality before traveling.
Cost accessibility
All-in surgical pricing in the range documented by medical tourism aggregators makes Korea a realistic destination for international patients who face multi-year waits or prohibitive costs in their home countries, particularly for DMEK, which is not uniformly available even in well-resourced health systems.
Key Takeaways
- Korea offers the full spectrum of corneal transplant techniques — PK, DALK, DSAEK, and DMEK — with technique selection driven by which corneal layer is diseased, not facility limitations.
- DSAEK and DMEK deliver faster visual rehabilitation and less astigmatism induction than full-thickness PK, but require highly trained surgeons — available at major Korean eye centers.
- International patients should plan a minimum 3–4 week in-country stay to cover mandatory early post-operative follow-up visits.
- Donor cornea supply is managed through a combination of domestic donation (regulated by MFDS) and international eye bank partnerships, reducing wait times compared to many Asian alternatives.
- Long-term rejection surveillance is required for years after surgery regardless of technique; Korean teams typically coordinate a handover plan with the patient's home ophthalmologist before discharge.
Frequently Asked Questions
Which technique is right for me — PK, DSAEK, or DMEK?
Technique selection depends on which corneal layer is damaged. Fuchs' dystrophy and bullous keratopathy affect only the endothelium and are typically treated with DSAEK or DMEK. Keratoconus and stromal scars may require DALK or full-thickness PK. Your Korean surgeon will determine the appropriate approach after reviewing your pre-operative diagnostics, including corneal topography and specular microscopy.
How long will I need to stay in Korea after surgery?
Most Korean eye centers require international patients to remain in-country for at least three to four weeks. Critical follow-up visits — confirming graft attachment, managing intraocular pressure, and assessing early rejection signs — occur at day one, week one, and around weeks three to four. DMEK patients may have additional early checks to confirm the tissue has unrolled and attached correctly before the air bubble resorbs.
What is corneal graft rejection and how is it managed?
Rejection occurs when the immune system recognizes the donor cornea as foreign and mounts an attack. Warning signs include sudden redness, increased light sensitivity, eye pain, and decreased vision. It can occur months or years after a technically successful transplant. Prompt treatment with intensive topical corticosteroid drops can usually reverse an early rejection episode. All keratoplasty patients remain on low-dose maintenance steroid drops long-term and must seek immediate ophthalmic review if rejection symptoms appear.
Can I have corneal transplant surgery if I have keratoconus?
Yes. Keratoconus that has progressed beyond what contact lenses or corneal cross-linking can manage is a recognized indication for transplantation. Deep anterior lamellar keratoplasty (DALK) is often preferred for keratoconus because it replaces the diseased front layers while preserving the patient's own endothelium, lowering the lifetime rejection risk compared to full-thickness PK.
How is donor cornea tissue sourced in Korea, and is the supply reliable?
Korea regulates donor tissue through the Ministry of Food and Drug Safety (MFDS), which sets standards for eye bank processing and tissue quality. Because domestic cornea donation rates in Asia are lower than in Western countries, major Korean transplant centers supplement supply through partnerships with international eye banks. Published trend data covering 2021–2023 shows this hybrid model supports ongoing surgical volume at leading centers.
Will I still need glasses after a corneal transplant?
Full-thickness PK grafts in particular can induce irregular astigmatism that may be managed with rigid gas-permeable contact lenses. Suture removal and adjustment over 12–24 months helps refine the refractive outcome. DSAEK and DMEK generally produce less astigmatism but glasses are still typical.
Related Topics
Sources
International Patient Preparation Guides
Independent resources for international patients researching care in South Korea:
Mencari informasi tentang perawatan di Korea?
KmedTour hanyalah sumber informasi. Hubungi rumah sakit secara langsung, atau cari rumah sakit yang terdaftar untuk merawat pasien asing di portal Medical Korea.
Quick Facts
Biaya
Minta perkiraan tertulis dari rumah sakit
Duration
10 days
Korean Hospitals
0+ Available
Rumah sakit yang menyediakan Cornea Transplantation
Medical Information Disclaimer
The information provided on this page about Cornea Transplantation is for general educational and informational purposes only. It is not intended as, and should not be construed as, medical advice, diagnosis, or treatment recommendations.
Always seek the advice of a qualified healthcare professional regarding any medical condition or treatment. Never disregard professional medical advice or delay seeking it because of information found on this website. Individual treatment outcomes may vary. Costs shown are estimates and may differ based on individual circumstances.
KmedTour is an independent information platform. It is not a medical provider or a registered foreign patient attraction agency, and it does not book treatment, take payment for treatment, or receive per-patient fees from hospitals. Treatment is arranged and paid for directly between you and the hospital.